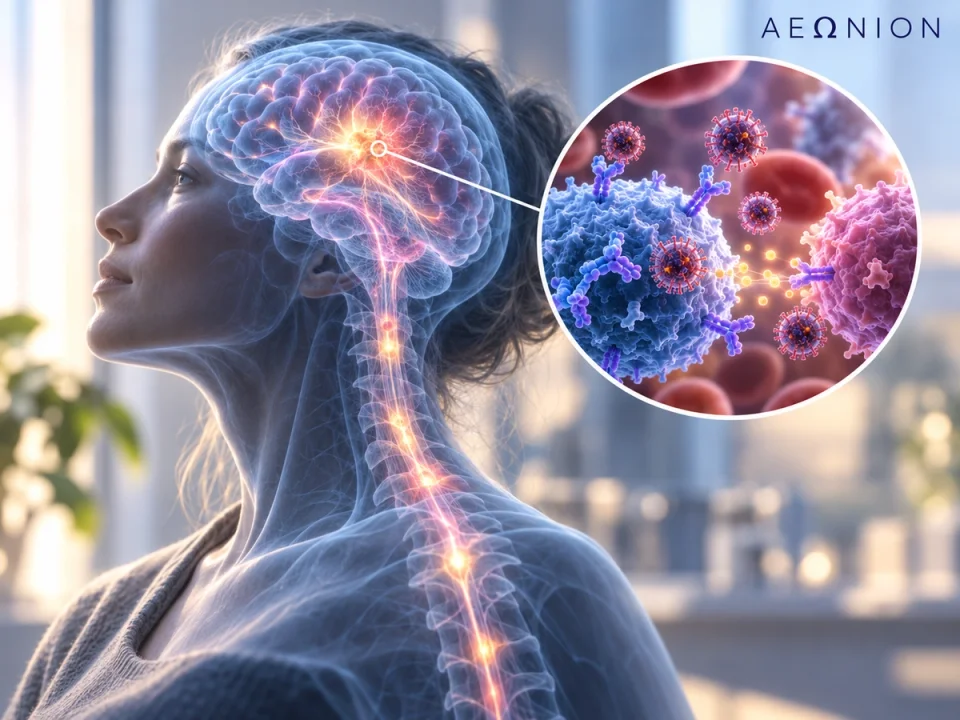
Multiple sclerosis relapses can appear unpredictable, with new neurological symptoms developing after months or years of relative stability. A new study suggests that part of the biological process may begin much earlier: researchers detected signs of Epstein–Barr virus reactivation and immune activation in the blood weeks to months before a relapse became clinically apparent.
The study, published in Nature Medicine, analyzed longitudinal blood samples from people with relapsing-remitting multiple sclerosis. Rather than comparing unrelated patients at a single point in time, the researchers used samples collected from the same individuals during periods of remission, before a relapse and, when available, during the relapse itself.
Epstein–Barr virus, or EBV, is a herpesvirus that establishes a lifelong infection after exposure. It persists largely inside B cells, a type of immune cell that produces antibodies but can also present antigens and influence other immune cells. EBV has already been strongly linked to the development of multiple sclerosis, but whether changes in viral activity help determine when an existing patient relapses has remained unclear.
Capturing the period before a relapse is difficult because researchers do not know in advance when one will happen. The team therefore used samples from the long-running CLIMB study at Brigham and Women's Hospital, which has followed people with MS for more than 25 years with blood collection, neurological examinations and MRI scans. Samples taken shortly before a later-confirmed relapse could then be identified retrospectively.
In total, the study incorporated 135 participants — 114 people with MS and 21 healthy controls — contributing 240 blood samples across several different analyses. Relapses were independently confirmed by two neurologists and required evidence of a contrast-enhancing lesion on MRI, helping ensure that the events represented active disease rather than symptoms alone.
The researchers first performed single-cell RNA sequencing on nearly 282,000 immune cells. This allowed them to examine how individual immune-cell populations changed depending on whether the blood had been collected during remission, before a relapse or during an active relapse.
The strongest immune disruption was not necessarily seen once symptoms had started.
Instead, widespread changes appeared during the pre-relapse period, with particularly strong alterations in monocytes, dendritic cells and several populations of B cells. In some immune populations, the transcriptional disturbance was actually greater before the relapse than during the clinically apparent attack.
B cells became a major focus of the study.
Among them, the researchers identified expansion and activation of populations resembling age-associated or atypical B cells, often called ABCs. These cells have previously been associated with autoimmune disease and chronic viral infections and showed increased expression of genes involved in antiviral responses, interferon signaling and antigen presentation before MS relapses.
The researchers then tested these findings using blood samples from an independent group of patients.
Among 23 people with paired remission and pre-relapse samples, ABC-like B cells increased before relapse in 21 of the 23 participants, with a median increase of approximately 1.6-fold.
More importantly, some of those B cells carried evidence of EBV activity.
The researchers measured gp350, a protein produced during the virus's lytic cycle, when EBV shifts from its dormant state toward active viral production. EBV gp350-positive B cells were rare overall, but their predicted frequency increased from about 0.19% of B cells during remission to 0.26% before relapse, an increase of more than 40%. The signal was strongest in samples collected within 90 days before symptoms appeared.
The team also looked directly for viral RNA.
In B cells isolated from another set of paired samples, they detected increased expression of LMP-1, an EBV gene capable of altering B-cell survival and signaling. Among 25 patients whose samples passed quality control, LMP-1 RNA was significantly more abundant before relapse than during remission.
LMP-1 is particularly interesting because it can activate signaling pathways inside B cells that promote survival, antigen presentation and inflammatory responses. The study found that related host signaling pathways were also elevated before relapse, providing another connection between viral activity and the altered immune state.
The researchers then asked whether the EBV-associated changes might interact with a person's inherited susceptibility to multiple sclerosis.
More than 200 genetic regions have previously been associated with MS risk, many of them affecting immune regulation and B-cell biology. In the new analysis, several of the B-cell populations that changed before relapse were also enriched for gene programs associated with MS genetic risk.
Some of those same regions overlapped with genomic sites regulated by EBNA-2, another Epstein–Barr virus protein that can influence human gene expression. The strongest overlap occurred in activated and atypical B-cell populations, suggesting a possible point where viral activity and inherited susceptibility converge inside the same immune cells.
Together, the findings support a model in which episodic EBV activity inside B cells could help shift the peripheral immune system into an inflammatory state before an MS relapse. That activated state could then contribute to events that eventually culminate in inflammation within the brain and spinal cord.
But the study does not establish that EBV reactivation causes MS relapses.
Because the researchers observed naturally occurring relapses rather than experimentally manipulating the virus, several alternative explanations remain possible. Subclinical inflammation in the central nervous system could begin first and subsequently activate the peripheral immune system and EBV. General B-cell activation could also cause dormant EBV to become more transcriptionally active, making viral reactivation a consequence or amplifier of the process rather than its original trigger.
The viral signals themselves were also small. EBV-positive cells represented only a tiny fraction of circulating B cells, and viral RNA was present at such low levels that sensitive amplification was required to detect it. The researchers also note that the gp350 assay requires further confirmation because low-frequency signals could potentially be affected by antibody cross-reactivity or non-specific binding.
The study nevertheless raises the possibility that future blood tests could detect a pre-relapse immune state before neurological symptoms emerge. The researchers suggest that combinations of EBV-related signals and abnormal B-cell populations could eventually be investigated as biomarkers for monitoring patients, although the current findings are not yet a validated relapse-prediction test.
It also strengthens interest in therapies directed specifically at EBV. Current B-cell-depleting treatments already reduce MS relapses, but they remove broad populations of B cells rather than selectively targeting EBV-infected cells. Whether antiviral drugs, vaccines or EBV-directed immune therapies could prevent relapses remains an open question and was not tested in this study.
Limits of the evidence
Although the overall study incorporated more than 100 people with MS, the most detailed single-cell analysis was based on only 15 of them, identified after screening 85 participants for the rare combination of samples taken at the right moments around a relapse. The researchers therefore validated different parts of the signal in additional cohorts using RNA sequencing, flow cytometry and viral RNA measurements, but no single analysis included the entire patient population.
The study was also observational. The fact that EBV-associated activity appeared before clinical relapse establishes an important temporal relationship, but it cannot determine whether viral reactivation initiates the relapse, amplifies another process that has already begun or simply occurs alongside it.
Only peripheral blood was examined. The researchers did not directly follow the same virus-associated B cells into the brain or spinal cord, so how the peripheral changes connect to the formation of new MS lesions remains unresolved.
The work therefore moves the EBV–multiple sclerosis connection from a question of who develops the disease toward the more immediate question of what happens before the disease becomes active again. The next step will be to determine whether EBV reactivation is an actual driver of those relapses — and whether interrupting it can prevent them before symptoms begin.
Limits of the evidence
Observational, so it cannot show that EBV reactivation causes relapses; the authors list at least three alternative models, including subclinical brain inflammation coming first, or general B-cell activation waking the virus as a bystander effect. The single-cell discovery analysis covered only 15 patients, found by screening 85. Viral signals were very small: EBV-positive cells were about 0.2% of B cells and viral RNA needed pre-amplification to detect. The authors note the gp350 assay lacked controls to exclude non-specific binding and needs orthogonal confirmation. Only blood was examined, never brain or spinal cord tissue. Not a validated relapse-prediction test.
Sources
- EBV reactivation priming of the peripheral immune system in multiple sclerosis relapse
King et al. · Nature Medicine · First online September 16, 2026 · Longitudinal observational study of 135 participants from the CLIMB cohort, using single-cell RNA sequencing, bulk transcriptomics, flow cytometry and viral RT-qPCR.
Disclosure
Supported by the US Department of Defense, the Water Cove Charitable Foundation and the Cindy Larsen-Chugg Chair, and by a Broad Institute Founders Grant and philanthropic support from George and Sandra K. Schussel. The funders had no role in study design, data collection and analysis, the decision to publish or manuscript preparation. Two senior authors declared industry ties: one reported research support from Genentech, Novartis, Octave Biosciences, Sanofi and Tiziana Life Sciences and consulting or advisory roles with Genentech, Lilly, Novartis, Octave Biosciences and Sanofi; the other reported advisory roles with Sanofi and Tiziana Life Sciences.


Discussion
Have a question about the research or a perspective to share?
Loading discussion…